Septic Pulmonary Embolism Due to Klebsiella pneumoniae Arising from Renal Vein Thrombosis
Background
Septic pulmonary embolism may arise when infected thrombotic material travels from an extrapulmonary venous source to the lungs. In this case, presumed hypervirulent Klebsiella pneumoniae pyelonephritis and renal abscesses were associated with renal vein–inferior vena cava septic thrombophlebitis and cavitary septic pulmonary emboli in a woman with untreated diabetes. A positive string test supported a hypermucoviscous phenotype, but hypervirulence was not genetically confirmed.
Data Highlights
Patient age: 47 years
Hemoglobin A1c: 14.7%
Duration of fever before presentation: 11 days
Positive string test: 11 mm
Blood-culture clearance: Day 7
Radiographic worsening: Day 10
Clinical and radiographic improvement: Day 38
Antimicrobial treatment completed: Day 49
Near-complete thrombus and emboli resolution: Day 117
Long-term recurrence: None more than 4 years after antimicrobial therapy ended
Key Findings
The patient presented with dysuria, prolonged fever, abdominal pain, and hypoxemia.
Blood and urine cultures grew Klebsiella pneumoniae, and bacteremia persisted despite meropenem.
The isolate was susceptible to ceftriaxone and levofloxacin and had a positive string test supporting a hypermucoviscous phenotype.
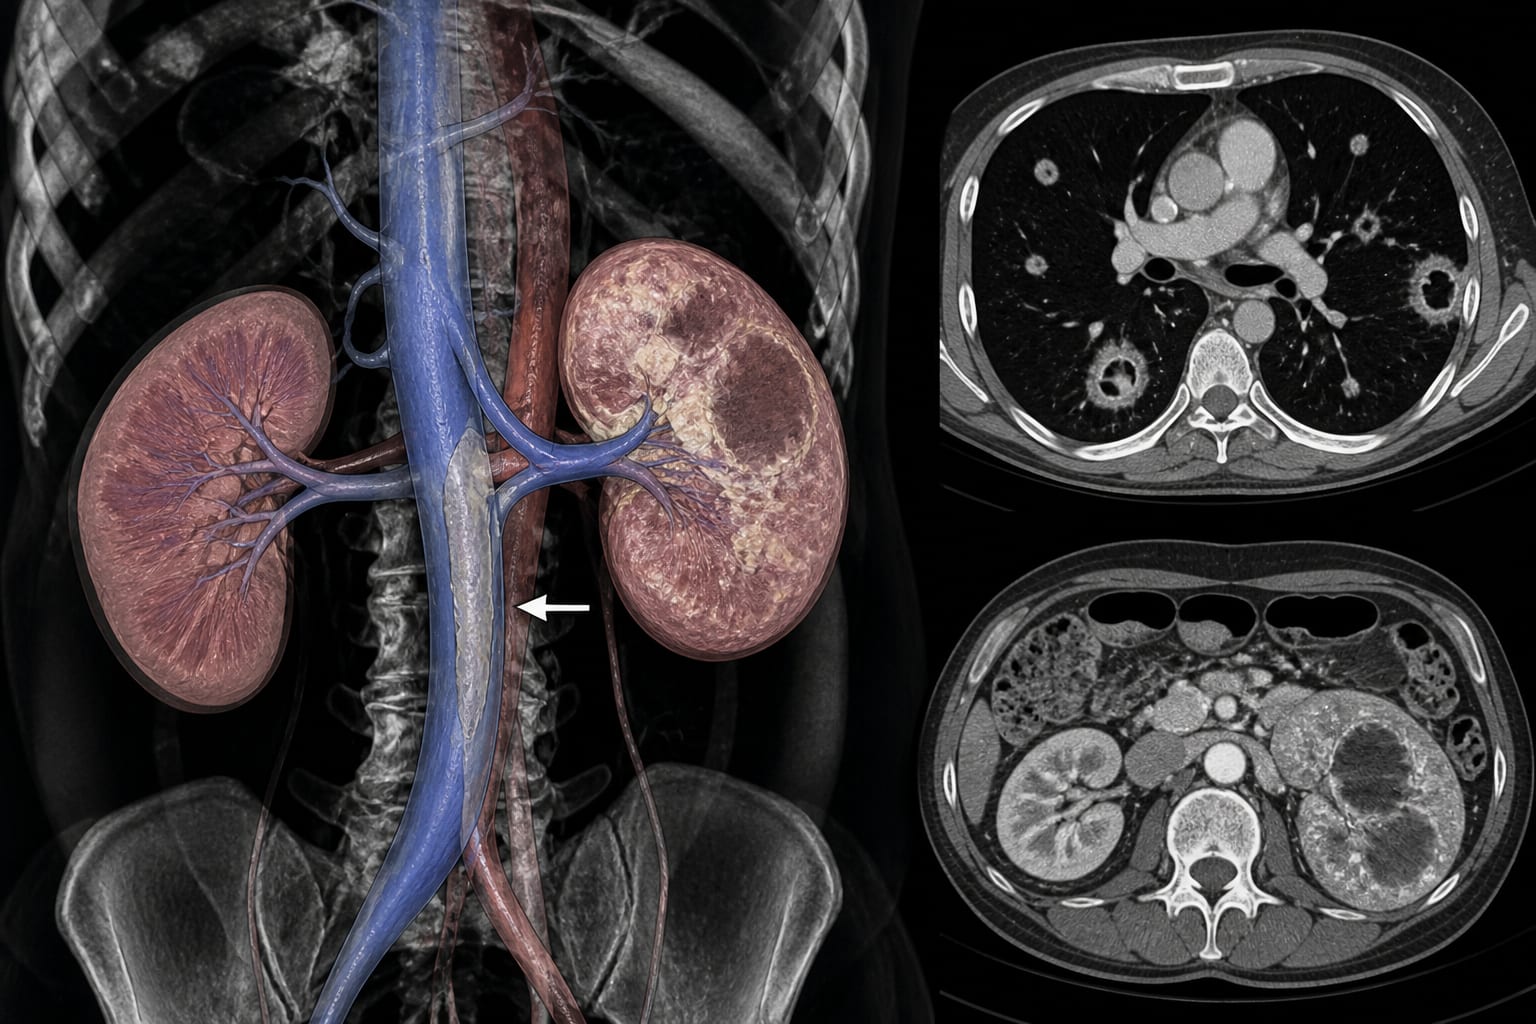
Contrast-enhanced CT showed left pyelonephritis, renal abscesses, a near-occlusive thrombus extending from the left renal vein into the inferior vena cava, pulmonary arterial emboli, and bilateral peripheral cavitary nodules.
Transesophageal echocardiography showed no vegetation.
Therapy was changed to ceftriaxone at meningitis dosing plus levofloxacin, with anticoagulation and insulin treatment.
CT findings worsened on day 10, but clinical, laboratory, and radiographic improvement by day 38 allowed nephrectomy, thrombectomy, and inferior vena cava filter placement to be avoided.
By day 117, the thrombus and septic pulmonary emboli had nearly resolved, allowing rivaroxaban to be discontinued.
Clinical Implications
Persistent Klebsiella pneumoniae bacteremia accompanied by peripheral cavitary pulmonary nodules should prompt evaluation for an occult septic venous source. Venous imaging may be particularly important when urinary infection, renal abscesses, diabetes, or negative echocardiography is present. A positive string test supports a hypermucoviscous phenotype but does not confirm genetic hypervirulence. Because this report describes one patient, its management outcome should not be generalized without caution.
Conclusion
Continued medical management with ceftriaxone, levofloxacin, anticoagulation, and insulin was followed by blood-culture clearance and near-complete resolution of the renal vein–inferior vena cava thrombus and septic pulmonary emboli without surgical intervention. More than 4 years after antimicrobial therapy ended, no infection, thrombosis, or septic pulmonary embolism had recurred.
Related Resources & Content
Klebsiella pneumoniae Septic Pulmonary Embolism From Renal Vein Thrombosis — Nojo M, Ohta S, Fukuda Y, et al. International Journal of Infectious Diseases. 2026;171:109006. doi:10.1016/j.ijid.2026.109006.
Renal Vein Thrombosis Secondary to Pyelonephritis: Targeting a Thrombo-Inflammatory Entity — Kounatidis D, Papadimitropoulos V, Vallianou N, et al. Clinics and Practice. 2024;14:1110–1122.
Pulmonary Septic Emboli: Diagnosis With CT — Kuhlman JE, Fishman EK, Teigen C. Radiology. 1990;174:211–213.
Septic Pulmonary Embolism: Presenting Features and Clinical Course of 14 Patients — Cook RJ, Ashton RW, Aughenbaugh GL, Ryu JH. Chest. 2005;128:162–166.
In a planned BALANCE analysis, elevated day 7 procalcitonin was associated with higher mortality, but the small subgroup analysis found no evidence that extending antibiotics from 7 to 14 days improved outcomes.