Clinical Scorecard: Association of Time to Surgery With Survival in Stage I Non–Small Cell Lung Cancer
At a Glance
Category
Detail
Condition
Stage I non–small cell lung cancer (NSCLC), adenocarcinoma or squamous cell carcinoma
Key Mechanisms
The study evaluated the association between diagnosis-to-resection time and overall survival; it did not assess biological mechanisms.
Target Population
Adults with clinical and pathologic stage I NSCLC treated with lobectomy or segmentectomy, without neoadjuvant or adjuvant therapy.
Care Setting
Preoperative evaluation and surgical care for early-stage NSCLC in a national cohort; the study supports prioritizing prompt evaluation and operative scheduling.
Key Highlights
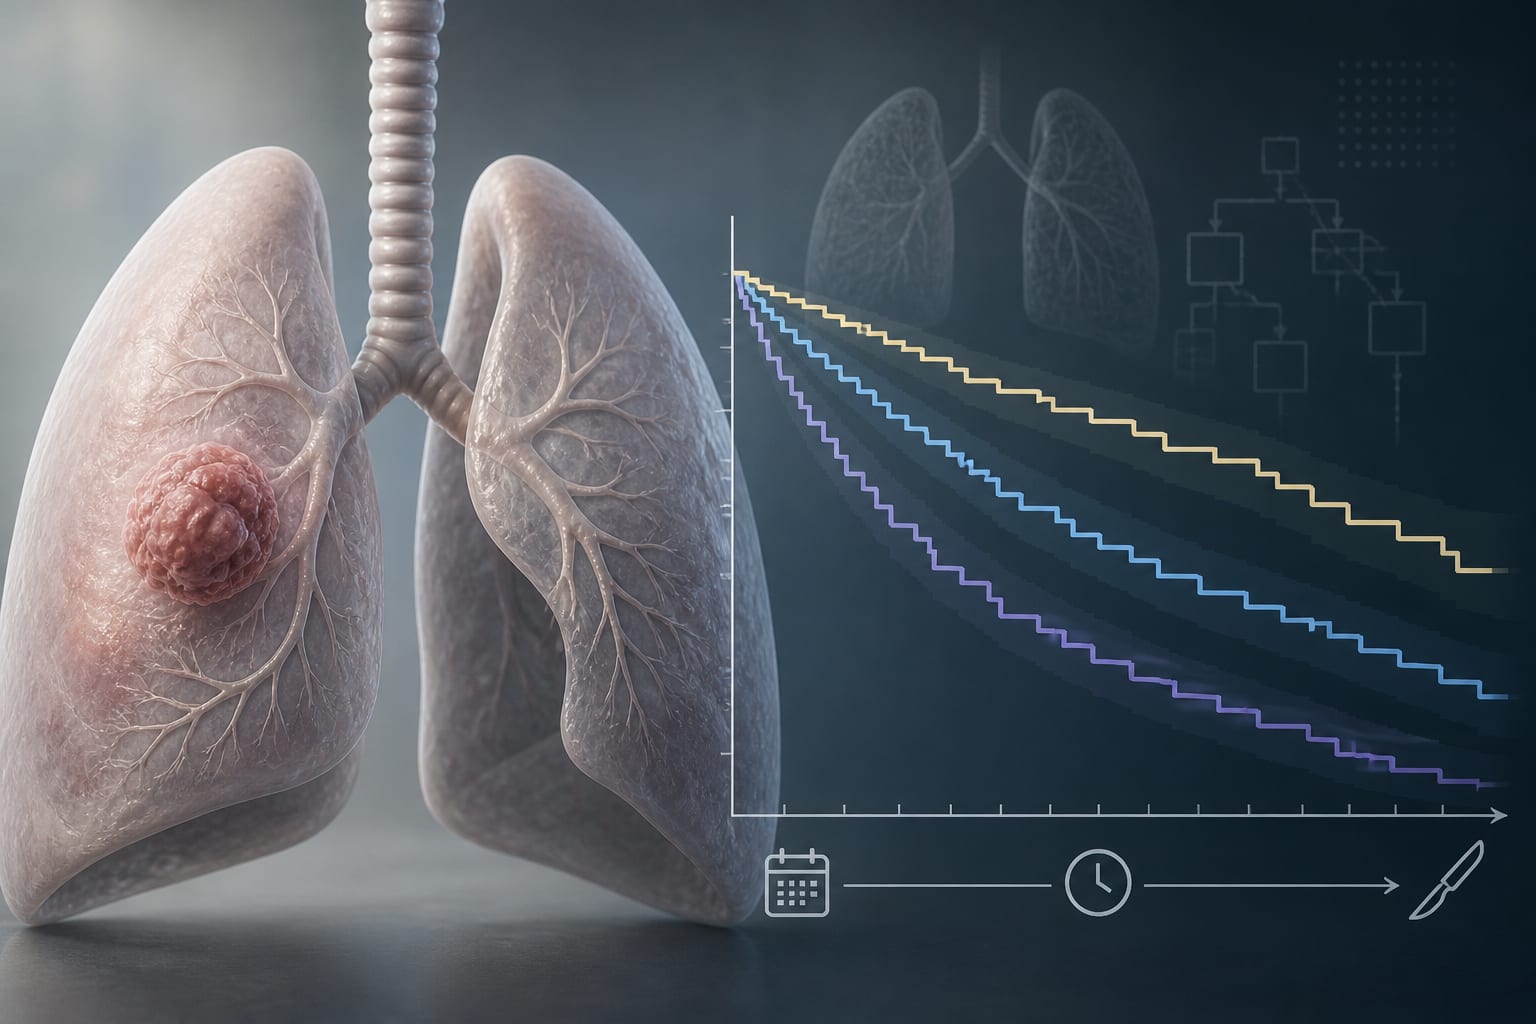
In this retrospective National Cancer Database cohort of 157,894 patients, median time from diagnosis to surgery increased from 23 days in 2004 to 43 days in 2022.
Adjusted mortality hazard was lowest when resection occurred approximately 2 to 4 weeks after diagnosis and increased subsequently.
Five-year overall survival was 74.1% for surgery within 4 weeks and 69.9% for surgery after 4 weeks in the matched cohort.
Treatment after 4 weeks was associated with Medicaid coverage, lack of insurance, non-Hispanic Black race, and care delivered at multiple facilities.
The authors note that the observational findings do not establish that delay itself caused poorer survival; residual confounding is possible.
Guideline-Based Recommendations
Diagnosis
The study included adults with clinical and pathologic stage I adenocarcinoma or squamous cell carcinoma; it does not provide diagnostic recommendations.
Management
The authors recommend prioritizing timely surgical resection, defined in this study as occurring within 4 weeks after diagnosis.
The authors support streamlined thoracic oncology pathways, including rapid-access clinics, integrated multidisciplinary pathways, and centralized referral systems.
Monitoring & Follow-up
The study assessed five-year overall survival and used Kaplan-Meier methods and multivariable Cox regression; it does not specify a clinical monitoring schedule.
Risks
Retrospective registry analysis may be affected by unmeasured confounding and lacked information on reasons for delay, tumor growth kinetics, and radiographic progression.
The authors caution that lower mortality during weeks 2 to 4 than during week 1 should not be interpreted as support for postponing surgery.
Patient & Prescribing Data
Adults with clinical and pathologic stage I NSCLC who underwent lobectomy or segmentectomy; patients receiving neoadjuvant or adjuvant therapy, with stage II to IV disease, time to treatment over 120 days, or unavailable survival data were excluded.
The study evaluated surgical timing, not medication prescribing. Resection within 4 weeks was associated with higher five-year overall survival than resection after 4 weeks; this observational association does not establish causation.
Clinical Best Practices
Prioritize efficient preoperative evaluation and operative scheduling for patients with stage I NSCLC.
Consider rapid-access clinics, integrated multidisciplinary pathways, and centralized referral systems as approaches proposed by the authors to facilitate timely resection.
Address structural barriers associated with longer time to surgery, including insurance coverage and care spanning multiple facilities.
Do not interpret the observed 2-to-4-week mortality nadir as a reason to delay surgery.
by Vikram Krishna, Claire Perez, Drew Bolster, Kellie Knabe, Raffaele Rocco, Philicia Moonsamy, Clark B. Fuller, Harmik J. Soukiasian, Andrew R. Brownlee