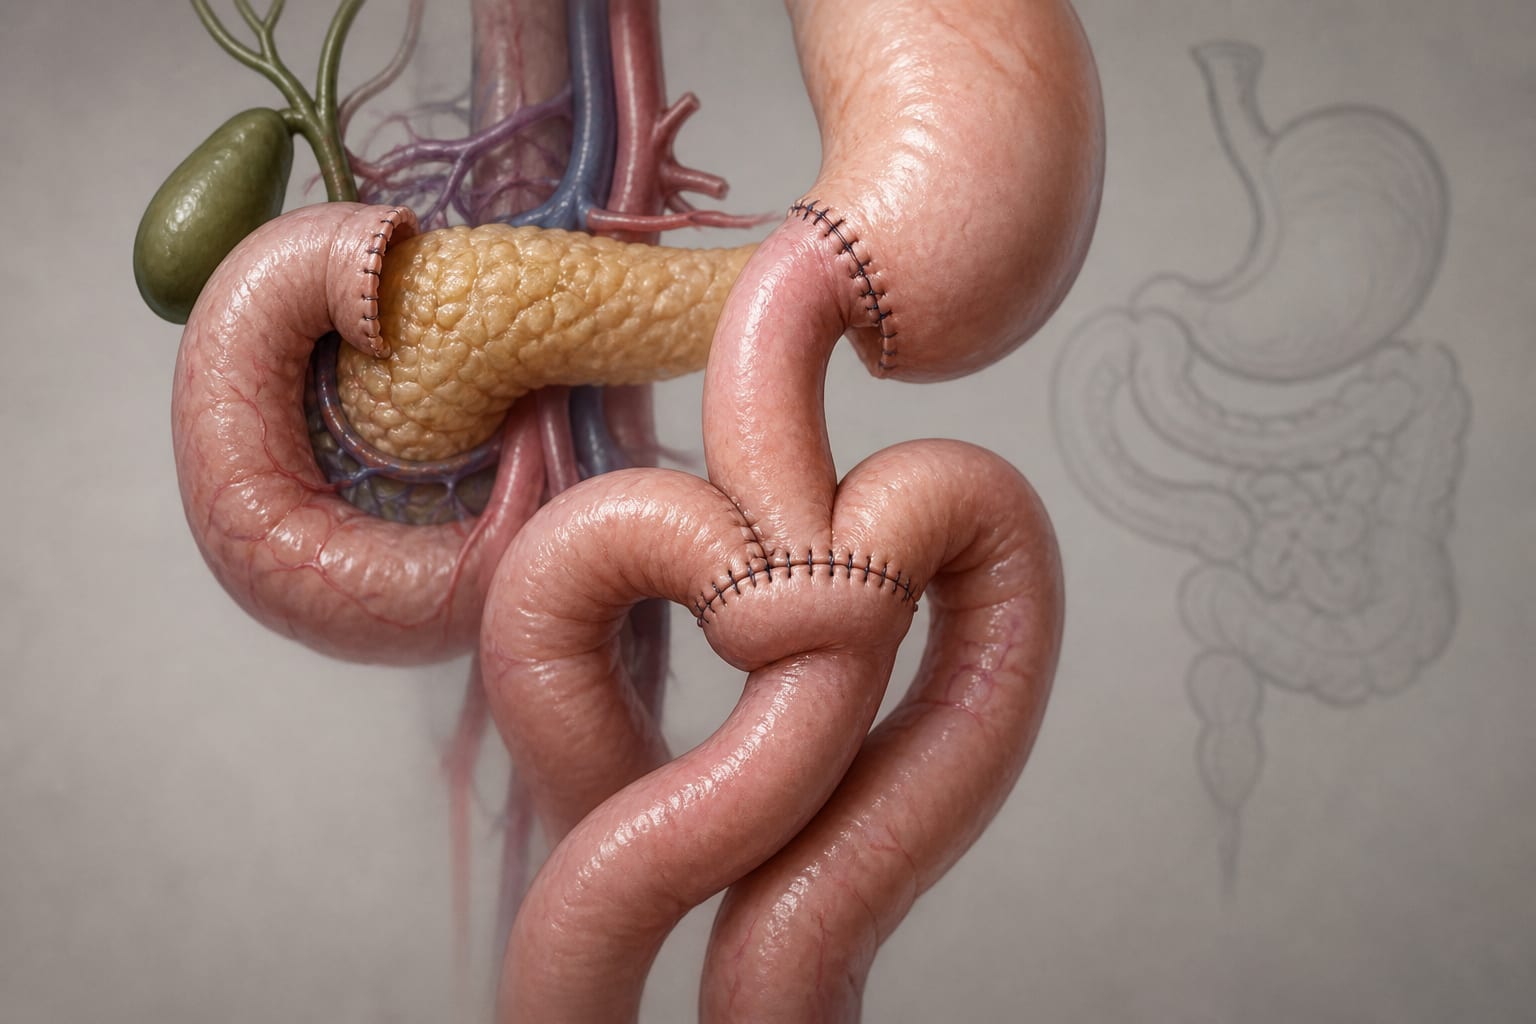
Efficacy and safety of Braun enteroenterostomy in patients undergoing pancreatoduodenectomy: a systematic review and meta-analysis - Scorecard - MDSpire
Clinical Scorecard: Assessment of Braun enteroenterostomy's effectiveness and safety in patients undergoing pancreatoduodenectomy: a systematic review and meta-analysis
At a Glance
Category
Detail
Condition
Delayed gastric emptying (DGE) after pancreatoduodenectomy (PD)
Key Mechanisms
Adjunctive Braun enteroenterostomy (BEE) may reduce DGE incidence by enhancing functional outflow through the gastrojejunostomy.
Target Population
Adults aged ≥18 years undergoing pancreatoduodenectomy for any indication.
Care Setting
Surgical and postoperative care for patients undergoing pancreatoduodenectomy.
Key Highlights
DGE occurs in approximately 30–60% of PD cases.
BEE aims to mitigate DGE and postoperative morbidity.
Inconsistent findings regarding BEE's effectiveness in reducing DGE.
Systematic review and meta-analysis conducted to synthesize recent studies.
Eligibility criteria included RCTs and cohort studies comparing PD with and without BEE.
Guideline-Based Recommendations
Diagnosis
DGE is diagnosed based on the inability to tolerate a regular diet or the need for a nasogastric tube for ≥10 days post-operation.
Management
Consider adjunctive BEE in patients undergoing PD to potentially reduce DGE.
Monitoring & Follow-up
Monitor for DGE and other postoperative complications such as pancreatic fistula.
Risks
Potential for increased morbidity and extended hospitalization due to DGE.
Patient & Prescribing Data
Adults undergoing pancreatoduodenectomy.
BEE may be performed based on surgeon preference or randomized allocation in clinical studies.
Clinical Best Practices
Utilize the ISGPS definition for grading DGE and POPF.
Assess intraoperative variables such as operative duration and estimated blood loss.
Evaluate postoperative outcomes including DGE and overall morbidity.
by Marios Alogakos, Ahmed Ghani, Stefan Bitar, Georgia Angeliniades, Konstantinos Manousidis, May Y. Hajeir, Lamees M. Al Darwashi, Christian A. Than, Hayato Nakanishi, Alexandra M. Roch, Eugene P. Ceppa