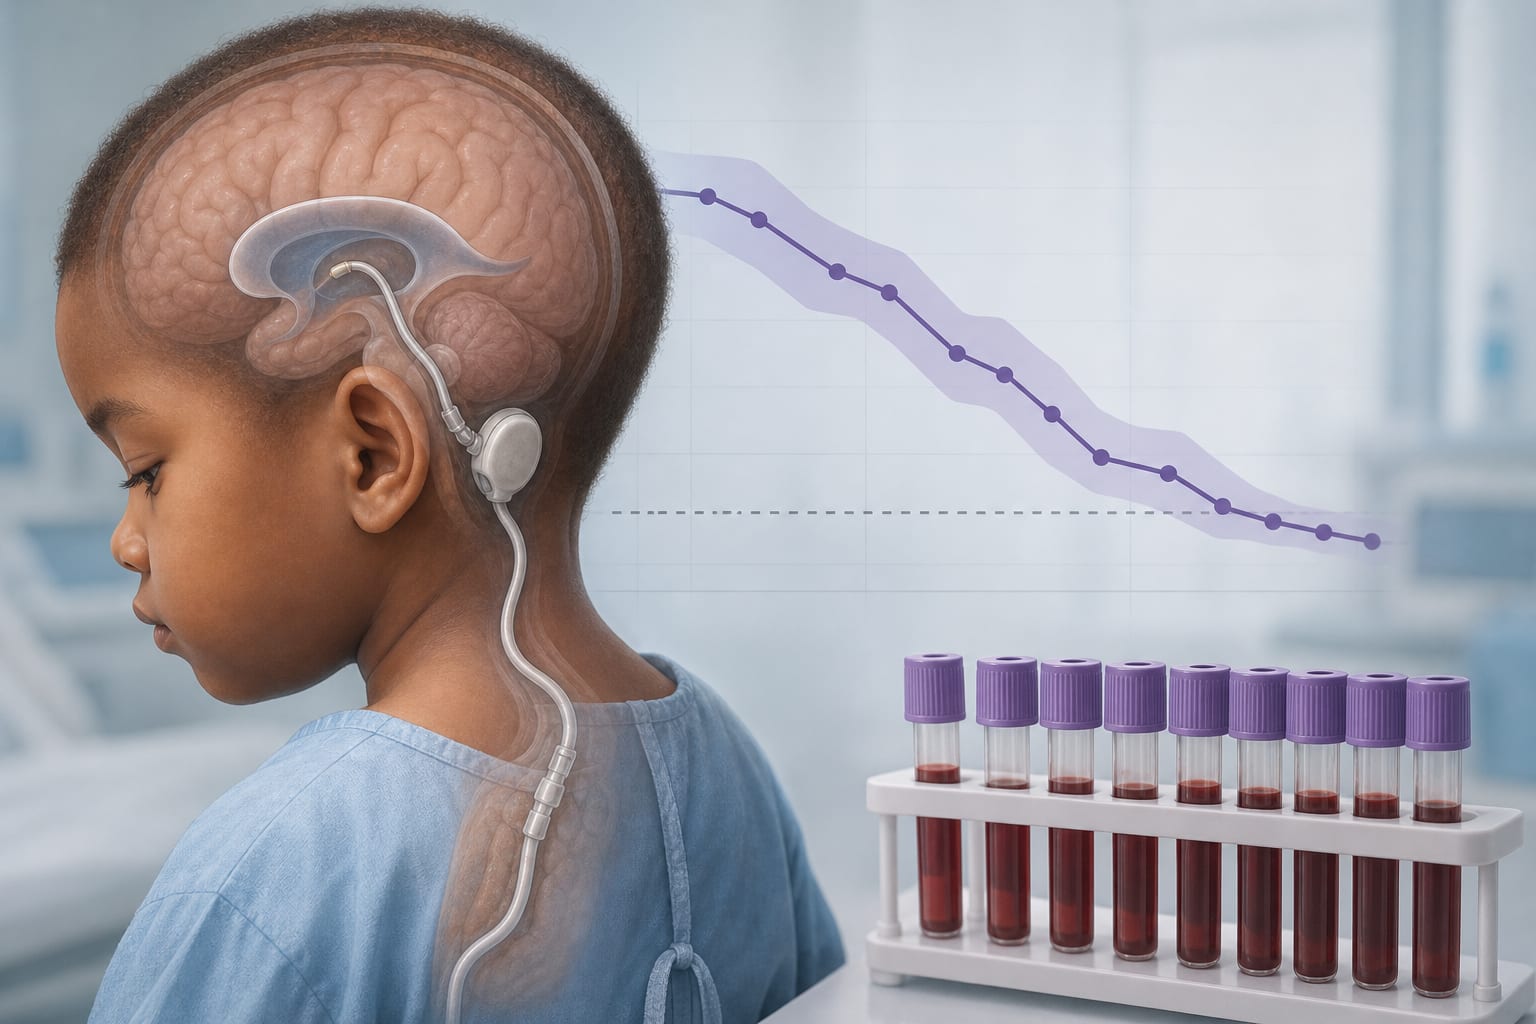
C-reactive Protein Changes During Antibiotic Treatment of Ventriculoperitoneal Shunt Infections in Children: A Retrospective Study
-
By
-
Kiara Rampershad
-
Zama Ndlondlo Princess Msibi
-
Basil Enicker
-
November 5, 2026
Clinical Scorecard: C-reactive Protein Changes During Antibiotic Treatment of Ventriculoperitoneal Shunt Infections in Children: A Retrospective Study
At a Glance
| Category | Detail |
|---|---|
| Condition | Clinical topic addressed by the source article: C-reactive Protein Changes During Antibiotic Treatment of Ventriculoperitoneal Shunt Infections in Children |
| Key Mechanisms | Hydrocephalus results from impaired cerebrospinal fluid production or absorption. The study reported biofilm-forming bacteria, particularly Staphylococcus epidermidis and Staphylococcus aureus, and antibiotic resistance in 58.6% of cultured organisms. |
| Target Population | Patients or participants described in the source article. |
| Care Setting | Care setting described in the source article. |
Key Highlights
- Mean admission CRP was 41.4 mg/L; 48% of children had admission CRP above 10 mg/L.
- Mean CRP increased to 49.4 mg/L by day 5; reported mean CRP declined from 48.6 to 29.4 mg/L between admission and day 30.
- A complete-case paired comparison found a difference in CRP between admission and day 30 (p=0.02). The Wilcoxon signed-rank test was not statistically significant, while log-transformed analysis showed a significant decline.
- Twenty-five children (17%) died; symptom duration of 7–30 days was reported to predict mortality (p=0.05). Age over 12 years was statistically associated with increased mortality risk (OR=8; the source does not provide the confidence interval).
- Antibiotic resistance was present in 58.6% of cultured organisms; reported biofilm-forming bacteria included Staphylococcus epidermidis and Staphylococcus aureus.
Guideline-Based Recommendations
Diagnosis
Management
- The authors state that CRP monitoring may support decisions about antibiotic duration, but the study does not establish a treatment-duration protocol.
- The authors recommend prioritising early shunt revision and prolonged postoperative care for biofilm or resistant infections; this is an author recommendation, not a guideline established by the study.
Monitoring & Follow-up
- The authors recommend routine CRP monitoring, particularly for patients with high-risk organisms; this is a recommendation for future work, not an evaluated monitoring protocol.
- Interpret CRP trajectories cautiously: distributions were right-skewed with outliers, follow-up was variable, and the admission-to-day-30 comparison did not model repeated measures or account for missingness.
Risks
Patient & Prescribing Data
Children with VP shunt-related meningitis; 147 patients met inclusion criteria, including 76 infants (51.7%).
Clinician-determined treatment durations were consistent with a mean antibiotic course of 27 days. The study did not establish an optimal antibiotic duration; CRP-guided treatment requires further study.
Clinical Best Practices
- The authors discuss serial CRP measurements during treatment; interpret values in light of skewness, outliers, and variable follow-up.
- The authors identify age, interval relative to shunt insertion, and underlying hydrocephalus aetiology as factors influencing CRP fluctuations.
- The authors recommend early shunt revision and prolonged postoperative care for biofilm or resistant infections; this recommendation was not tested as a comparative intervention in the study.
- The authors identify comparison of CRP, white blood cell count, and procalcitonin for identifying paediatric VP shunt infections as an area for further study.
Related Resources & Content
Based on findings from:
Role of C-reactive protein response to antibiotic therapy in children with a ventriculo-peritoneal shunt infection: a retrospective study
Kiara Rampershad, Zama Ndlondlo Princess Msibi, Basil Enicker. Bmj Paediatrics Open, 2026.
https://bmjpaedsopen.bmj.com/content/10/1/e004408
This content is an AI-generated, fully rewritten summary based on a published scholarly article. It does not reproduce the original text and is not a substitute for the original publication. Readers are encouraged to consult the source for full context, data, and methodology.