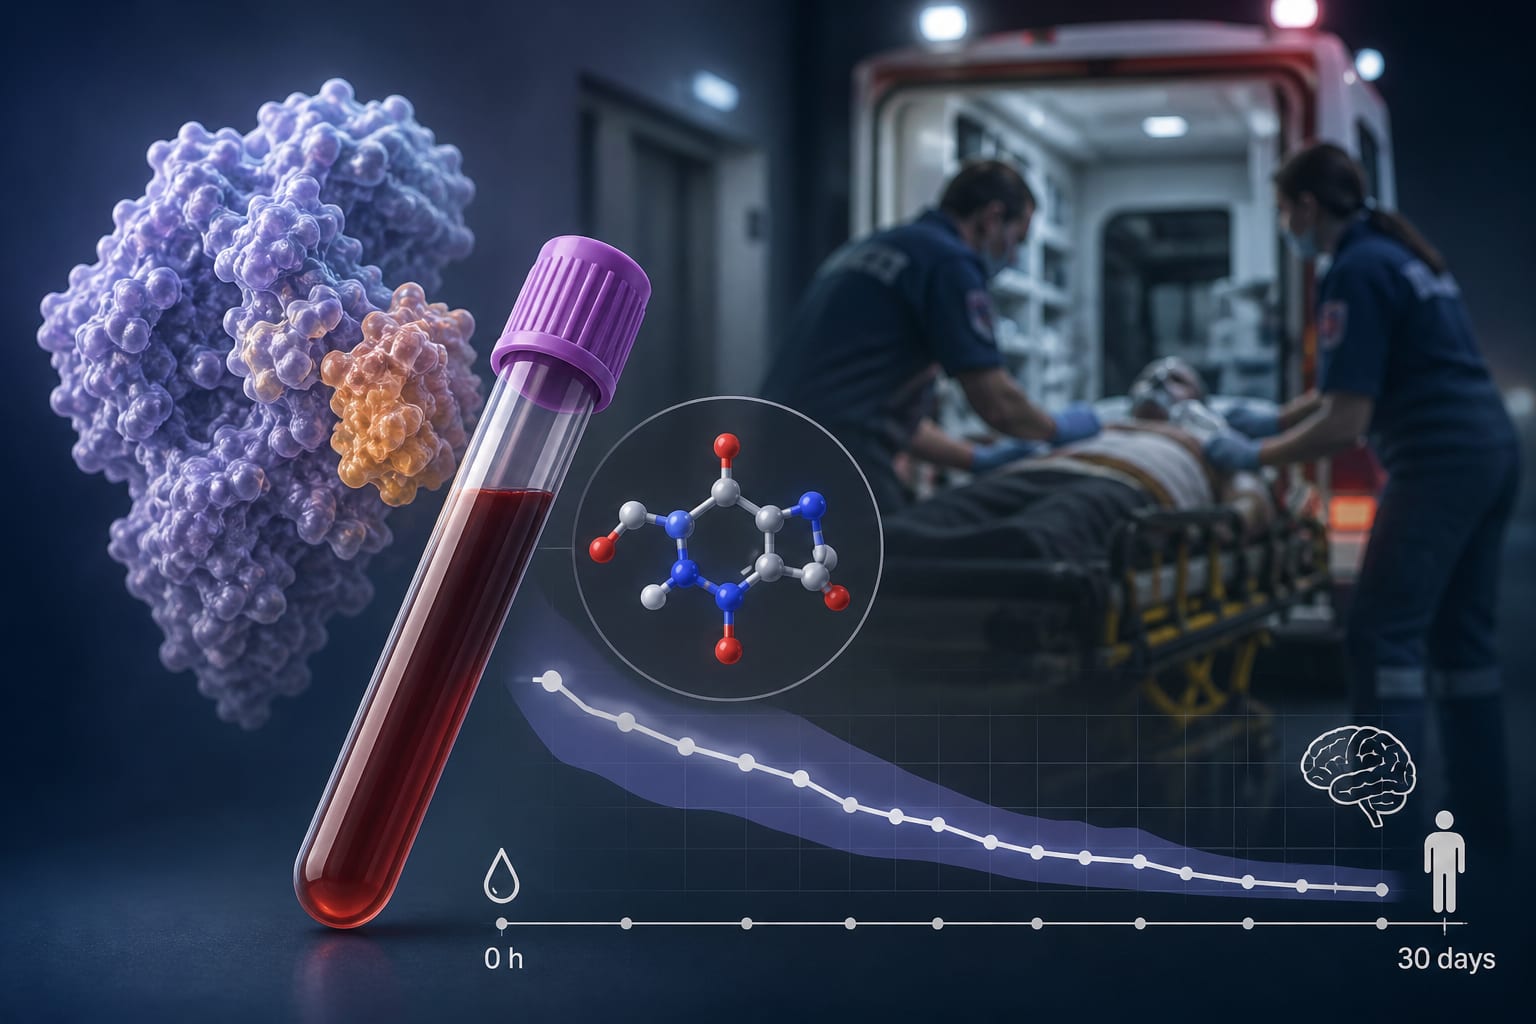
To assess whether serum uric acid (UA) change during the first 24 hours after out-of-hospital cardiac arrest (OHCA) is associated with 30-day survival and neurological outcome.
Approach:
Design and population: Prospective, multicenter observational study of 375 patients in the SOS-KANTO 2017 cohort with UA measured at hospital arrival and 24 hours after cardiac arrest.
Exposure and outcomes: UA decline was calculated as the percentage decrease from arrival to 24 hours. Outcomes were 30-day survival and good neurological status (Cerebral Performance Category 1 or 2).
Analysis: Associations were assessed using adjusted models accounting for patient, arrest, and institutional factors; additional analyses considered renal comorbidity and temperature control.
Key Findings:
Of 375 patients, 209 survived to 30 days and 166 did not.
Median admission UA was similar in survivors and non-survivors, while median UA decline was greater among survivors: 21% versus 2.5% (p<0.001).
Each 10-percentage-point greater UA decline was associated with higher odds of 30-day survival (adjusted OR 1.10; 95% CI 1.00–1.20; p=0.048).
The association with survival persisted in an analysis accounting for temperature control and pre-arrest renal comorbidity (adjusted OR 1.09; 95% CI 1.01–1.19; p=0.04).
Greater UA decline was also associated with good neurological outcome (adjusted OR 1.19 per 10-percentage-point increase; 95% CI 1.05–1.35; p=0.006).
Interpretation:
The authors report that early serum UA decline was associated with 30-day survival and good neurological outcome. The study does not establish that this association is independent of renal dysfunction or identify the physiological processes underlying the UA trajectory.
Limitations:
Serial renal-function measurements and urine-output data were unavailable, limiting assessment of renal dysfunction’s contribution.
Requiring UA measurements at both time points excluded patients without a 24-hour measurement, including some who died early; the direction and extent of resulting selection bias are unknown.
Detailed causes of death were unavailable, preventing attribution of the association to specific mechanisms.
UA decline and lactate clearance were measured over different intervals, so their prognostic performance could not be directly compared.
Conclusion:
Early UA decline was associated with short-term survival and favorable neurological outcomes after OHCA. The authors call for prospective validation alongside renal, metabolic, hemodynamic, and neurological measures.
November 4, 2026 | Gennaro Giustino, MD, structural interventional cardiologist at Atlantic Health, emphasizes the distinction between identifying disease and fully understanding its structural implications.