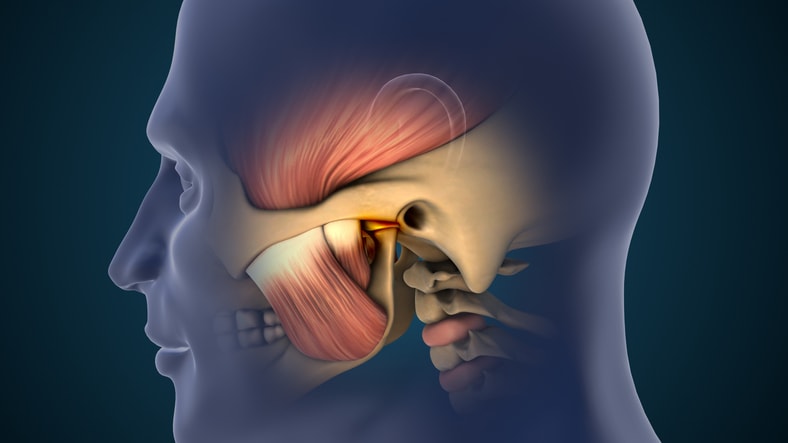
To compare jaw function and sleep quality among people with psoriasis, including by psoriatic arthritis (PsA) status and systemic treatment, and with healthy controls.
Approach:
Design and participants: Prospective, controlled cross-sectional study of 105 patients with psoriasis and 73 age- and sex-matched controls.
Measures: Jaw function was assessed with the JFLS-20, sleep quality with the PSQI, and skin disease severity with PASI. Analyses compared treatment groups and PsA status, with adjustment for specified demographic and disease factors.
Key Findings:
Patients with PsA had higher mean JFLS-20 scores than those without PsA (0.80 vs. 0.45); PsA remained independently associated with greater jaw limitation in adjusted analyses.
Overall, jaw limitation was not significantly greater in the psoriasis group than in controls. Mean JFLS-20 scores ranged from 0.51 to 0.59 across psoriasis treatment groups, compared with 0.52 in controls.
Higher PASI scores were independently associated with poorer sleep quality, while biologic treatment status was associated with better sleep quality. PsA was not independently associated with sleep quality.
Poor sleep quality was reported by 60% of patients receiving no systemic therapy and 60% receiving nonbiologic systemic therapy, compared with 7% receiving biologics and 10% of controls.
Exploratory comparisons within the PsA group found lower mean jaw limitation and PSQI scores among biologic-treated patients, but could not establish that treatment caused these differences.
Interpretation:
The authors identified PsA-associated temporomandibular functional limitation as the study’s principal novel finding. Sleep quality was associated with skin disease severity and biologic treatment status in adjusted analyses.
Limitations:
Single-center, cross-sectional design and relatively small sample.
Patient-reported questionnaires were used without objective dental examinations, imaging, or sleep monitoring.
Factors influencing sleep were not assessed in detail; exploratory subgroup comparisons were not adjusted for multiple testing.
Lower disease activity among biologic-treated patients complicates interpretation of treatment associations.
The biologic cohort excluded tumor necrosis factor inhibitors.
Conclusion:
The study authors reported no conflicts of interest.
Application of newly proposed GRAPPA and EULAR criteria in a longitudinal cohort identified progressively smaller groups of patients with early psoriatic arthritis who experienced persistently worse patient-reported outcomes.