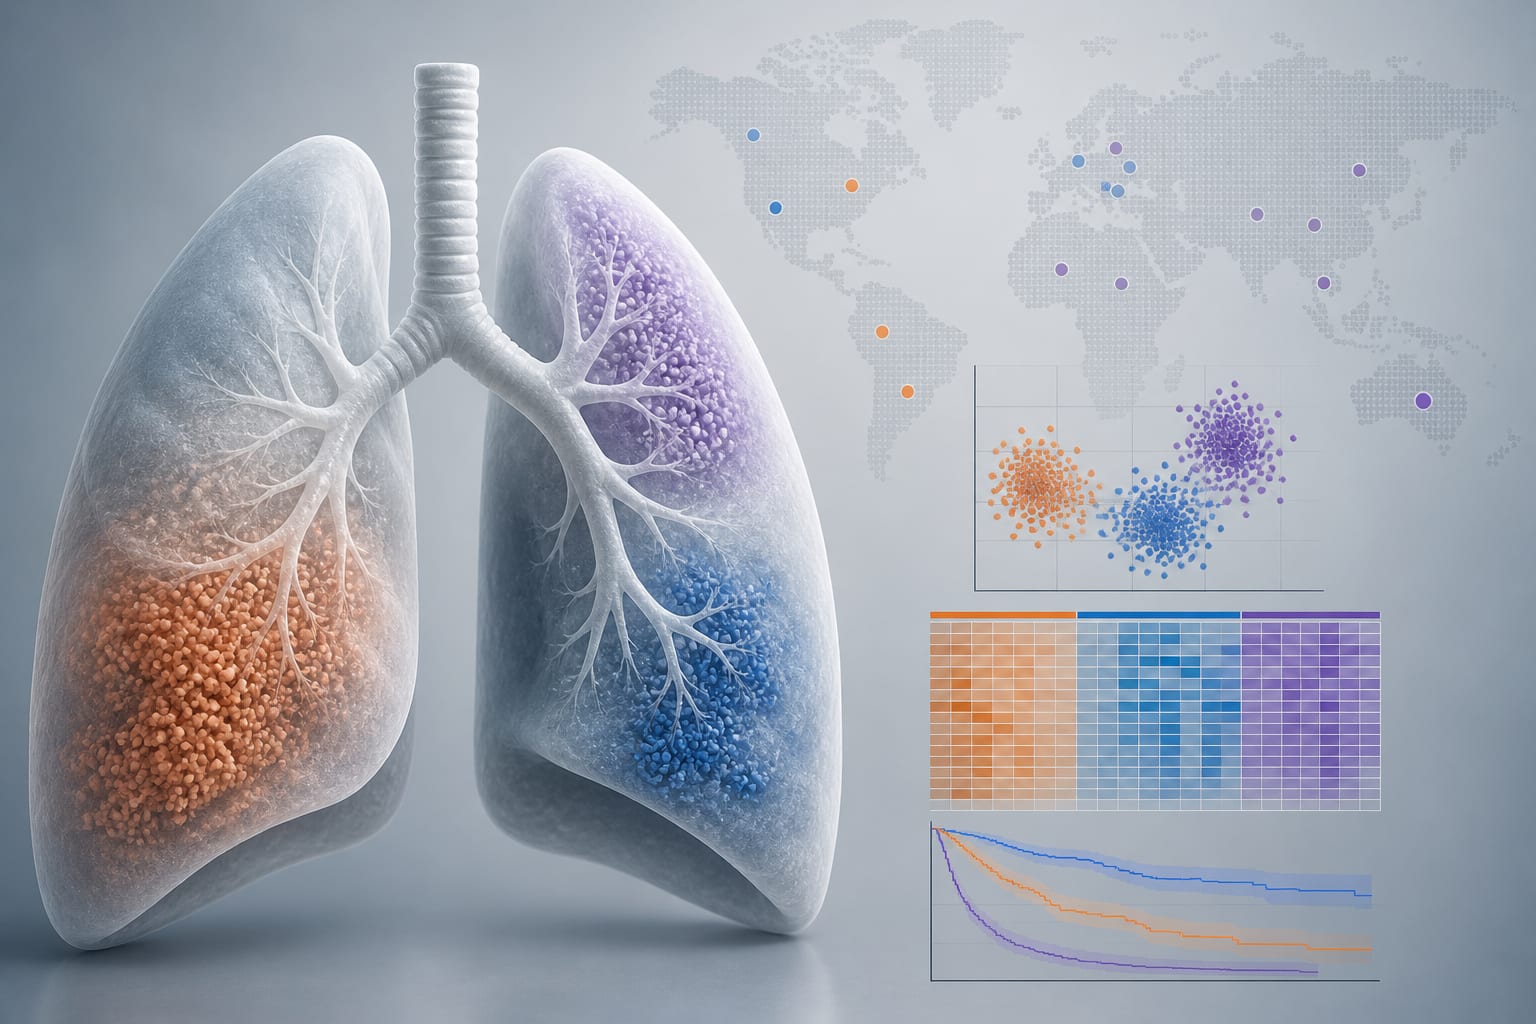
The article examines the objective, findings, and clinical context described in A Practical Approach to ARDS Phenotyping Using the International POLARIS Cohort.
Approach:
Phenotyping principles: The article proposes that useful phenotypes should have mechanistic grounding, inform specified decisions, and be generalizable across care settings.
Complementary methods: Biomarker panels provide biologically grounded inflammatory classification, while clinical classifiers infer phenotypes from routinely collected data without specialized assays.
POLARIS design: POLARIS enrolls patients across academic, community, and private hospitals in high- and low-resource settings, using eligibility criteria based on the 2023 Global Definition of ARDS.
Key Findings:
Retrospective analyses have reported heterogeneous treatment effects associated with fluid management, simvastatin, and corticosteroids across inflammatory phenotypes.
Prospective biomarker studies demonstrate implementation challenges: PHIND had low recruitment per center, and SPARC classified about 80% of patients during its final phase despite dedicated laboratory workflows.
Clinical classifiers may improve accessibility but can reflect differences in institutional practice, testing frequency, and missing-data patterns, creating risks of model drift.
POLARIS will assess whether routine-data inflammatory phenotypes predict 28-day mortality, distinguish responses to early intravenous corticosteroids within a prespecified causal framework, and remain reproducible across healthcare systems.
Interpretation:
The article presents biomarker-based and clinical phenotyping as complementary approaches: biomarkers support biological fidelity, while clinical classifiers are intended to assess whether phenotyping can be extended to routine care. Both approaches require rigorous prospective evaluation.
Limitations:
The provided context describes POLARIS objectives but does not report cohort results.
The context ends mid-sentence, so additional planned dimensions or qualifications may be omitted.
Conclusion:
The article argues that prospective implementation and generalizability should be considered from the outset, while recognizing that clinical classifiers require validation across settings.