Identify the most likely diagnosis and describe the management reported for a patient with Crohn’s disease receiving infliximab.
Approach:
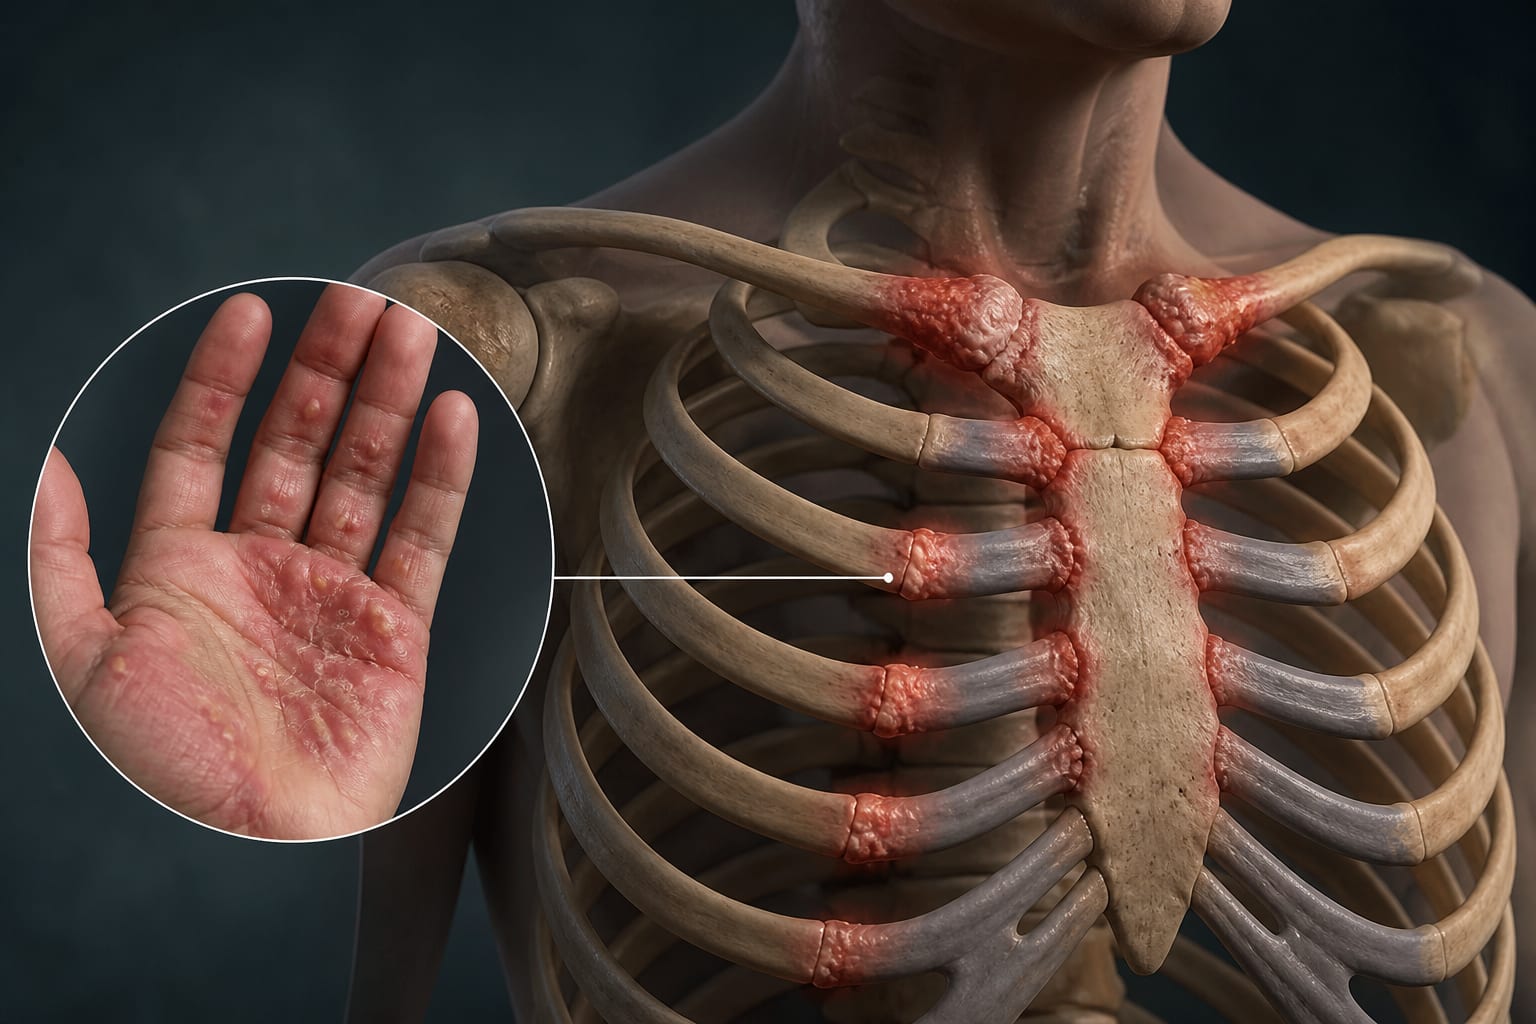
Clinical assessment: A 28-year-old man with ileal Crohn’s disease in clinical remission on infliximab–azathioprine therapy developed palmoplantar papules and pustules, followed by acneiform eruptions and acute chest pain after his sixth infliximab infusion.
Investigations: ECG, serum troponin and stress echocardiography were unremarkable. Chest MRI showed manubriosternal bone marrow oedema with mild adjacent soft-tissue inflammation; infectious causes were excluded.
Management: Gastroenterology, dermatology and rheumatology specialists collaborated in management with NSAIDs, methotrexate and topical corticosteroids. Ustekinumab was considered as an alternative, but infliximab was continued.
Key Findings:
The patient met criteria for SAPHO syndrome, supported by axial osteitis, preceding palmoplantar pustulosis and subsequent acneiform eruptions.
Treatment with NSAIDs, methotrexate and topical corticosteroids resulted in complete chest-pain resolution and partial improvement of the skin lesions.
Infliximab was continued; intermittent topical corticosteroids were used for the skin lesions, and chest pain did not recur.
Interpretation:
Anti-TNF-induced SAPHO syndrome was considered more likely than paradoxical psoriasis alone, which did not fully explain the osteoarticular findings.
Limitations:
This is a single-patient case report.
The source provides no comparative evidence to establish the relative effectiveness of the treatments.
Conclusion:
The authors emphasize awareness of SAPHO syndrome in patients with inflammatory bowel disease receiving anti-TNF therapy and describe multidisciplinary management of this case.