Disseminated Sporotrichosis Presenting as Tuberculosis in an Immunocompetent Patient: Challenges in Regions Endemic to Tuberculosis
-
By
-
Natthapong Suthammopasut
-
Athitaya Luangnara
-
September 8, 2026
Objective:
To report a case of disseminated sporotrichosis that closely mimicked tuberculosis in a patient without overt immunodeficiency in a tuberculosis-endemic setting.
Approach:
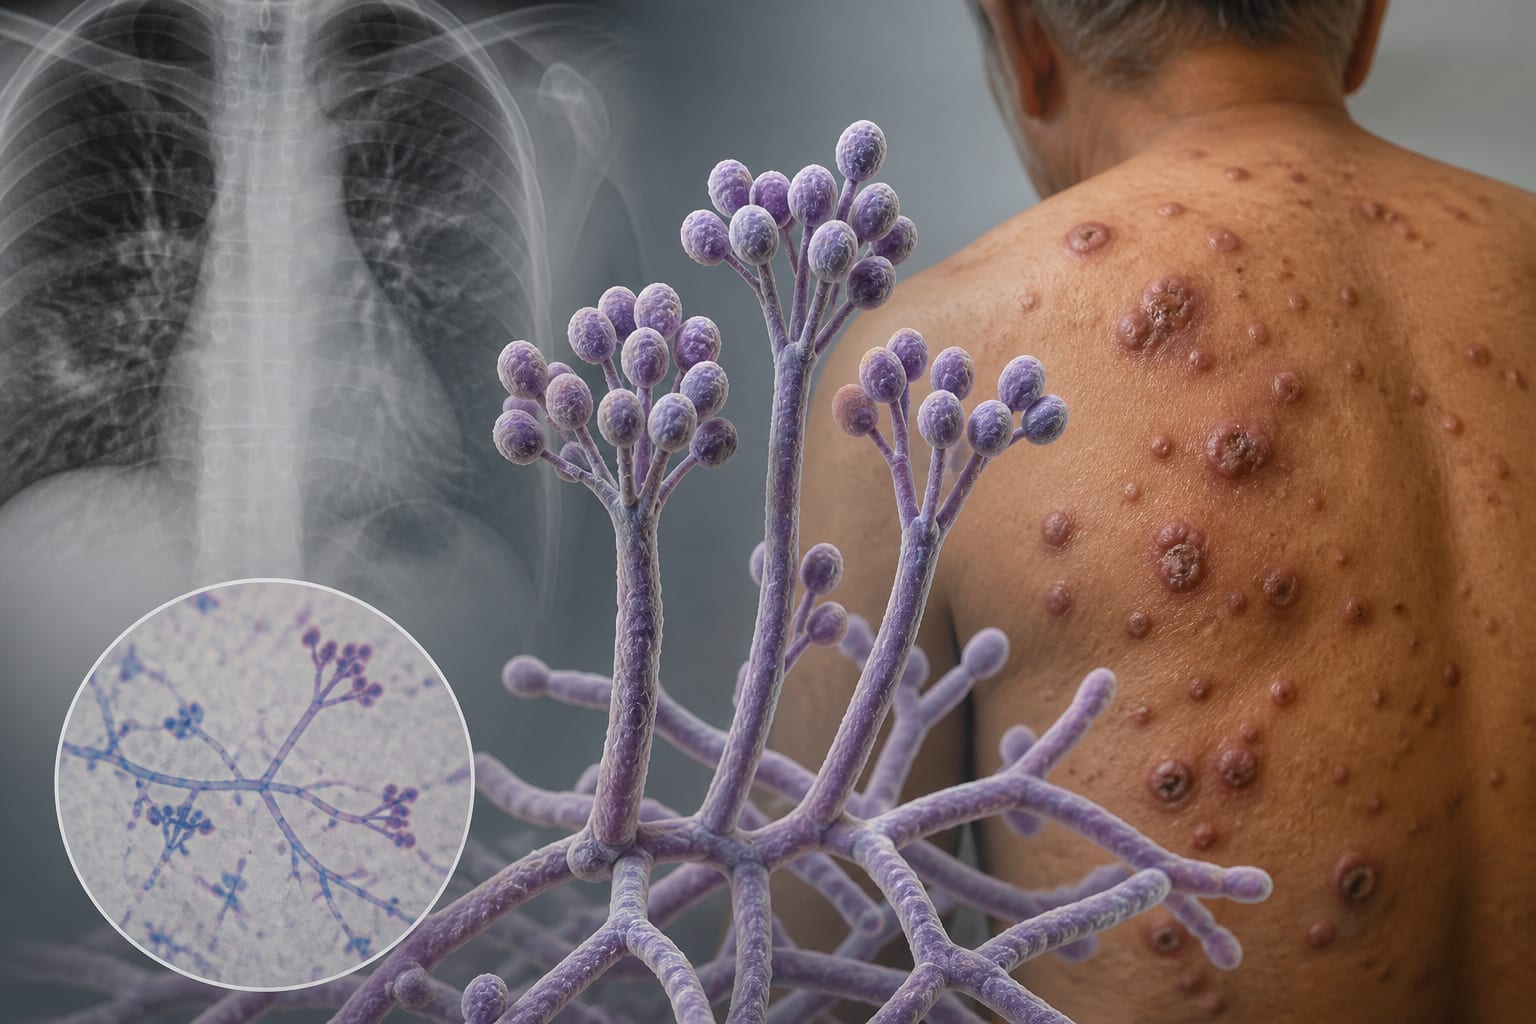
- Case Presentation: A 78-year-old man with treated diffuse large B-cell lymphoma in complete remission for 10 years presented with multiple painful subcutaneous nodules initially confined to the right forearm for 2 months. The lesions enlarged and spread to the left forearm, chest, abdomen, back, and face, later ulcerating and draining pus. He subsequently developed mild productive cough, fatigue, anorexia, and unintentional weight loss. Initial biopsy showed granulomatous inflammation with central suppuration, but multiple stains did not identify organisms.
- Diagnosis and Treatment: Because tuberculosis was endemic in the region and granulomas were present, standard anti-tuberculous therapy with isoniazid, rifampicin, pyrazinamide, and ethambutol was started. Lesions continued to progress despite adherence. Repeat biopsy again showed granulomatous inflammation without visualized organisms, but fungal culture grew pigmented colonies identified as Sporothrix schenckii complex. The patient received amphotericin B deoxycholate, which was changed to liposomal amphotericin B after acute kidney injury, followed by oral itraconazole for a total of 12 months.
Key Findings:
- Disseminated sporotrichosis may resemble tuberculosis and create substantial diagnostic difficulty, particularly in tuberculosis-endemic regions.
- Direct smears may fail to detect organisms because fungal cells can be sparse; fungal culture is considered the diagnostic gold standard but typically requires 1 to 2 weeks.
- Current guidelines cited by the authors recommend itraconazole as first-line therapy, with amphotericin B considered for induction in severe disease. At least 12 months of total treatment is generally recommended for disseminated infection.
- Identification of risk factors and a broad differential diagnosis are important when disseminated sporotrichosis presents with granulomatous inflammation that resembles tuberculosis or other infections.
Interpretation:
This case illustrates how disseminated sporotrichosis can be mistaken for tuberculosis in an endemic setting, particularly when granulomatous inflammation is present and organisms are not detected on direct staining. The authors emphasize maintaining a high index of suspicion and identifying relevant risk factors to broaden the differential diagnosis.
Limitations:
- Molecular techniques for species-level identification were unavailable, so the isolate could only be identified phenotypically as belonging to the Sporothrix schenckii complex, limiting species-level epidemiological interpretation.
- Sporotrichosis was not microbiologically confirmed in the cats, so presumed zoonotic transmission was based on the patient’s exposure history and lesion distribution and remained speculative.
- Pulmonary involvement was presumed from the clinical and radiological response to antifungal treatment without microbiological or histopathological confirmation from respiratory specimens.
Conclusion:
The patient’s cutaneous lesions healed, pulmonary lesions and abscesses markedly regressed, and no active skin lesions or respiratory symptoms remained at 12 months after antifungal therapy. The case underscores the diagnostic challenge of sporotrichosis in tuberculosis-endemic settings and the importance of comprehensive history taking for possible risk factors.
Based on findings from:
Disseminated sporotrichosis masquerading as tuberculosis in a patient without overt immunodeficiency: challenges in tuberculosis-endemic area
Natthapong Suthammopasut, Athitaya Luangnara. International Journal Of Infectious Diseases, 2026.
https://www.sciencedirect.com/science/article/pii/S1201971226006909
This content is an AI-generated, fully rewritten summary based on a published scholarly article. It does not reproduce the original text and is not a substitute for the original publication. Readers are encouraged to consult the source for full context, data, and methodology.