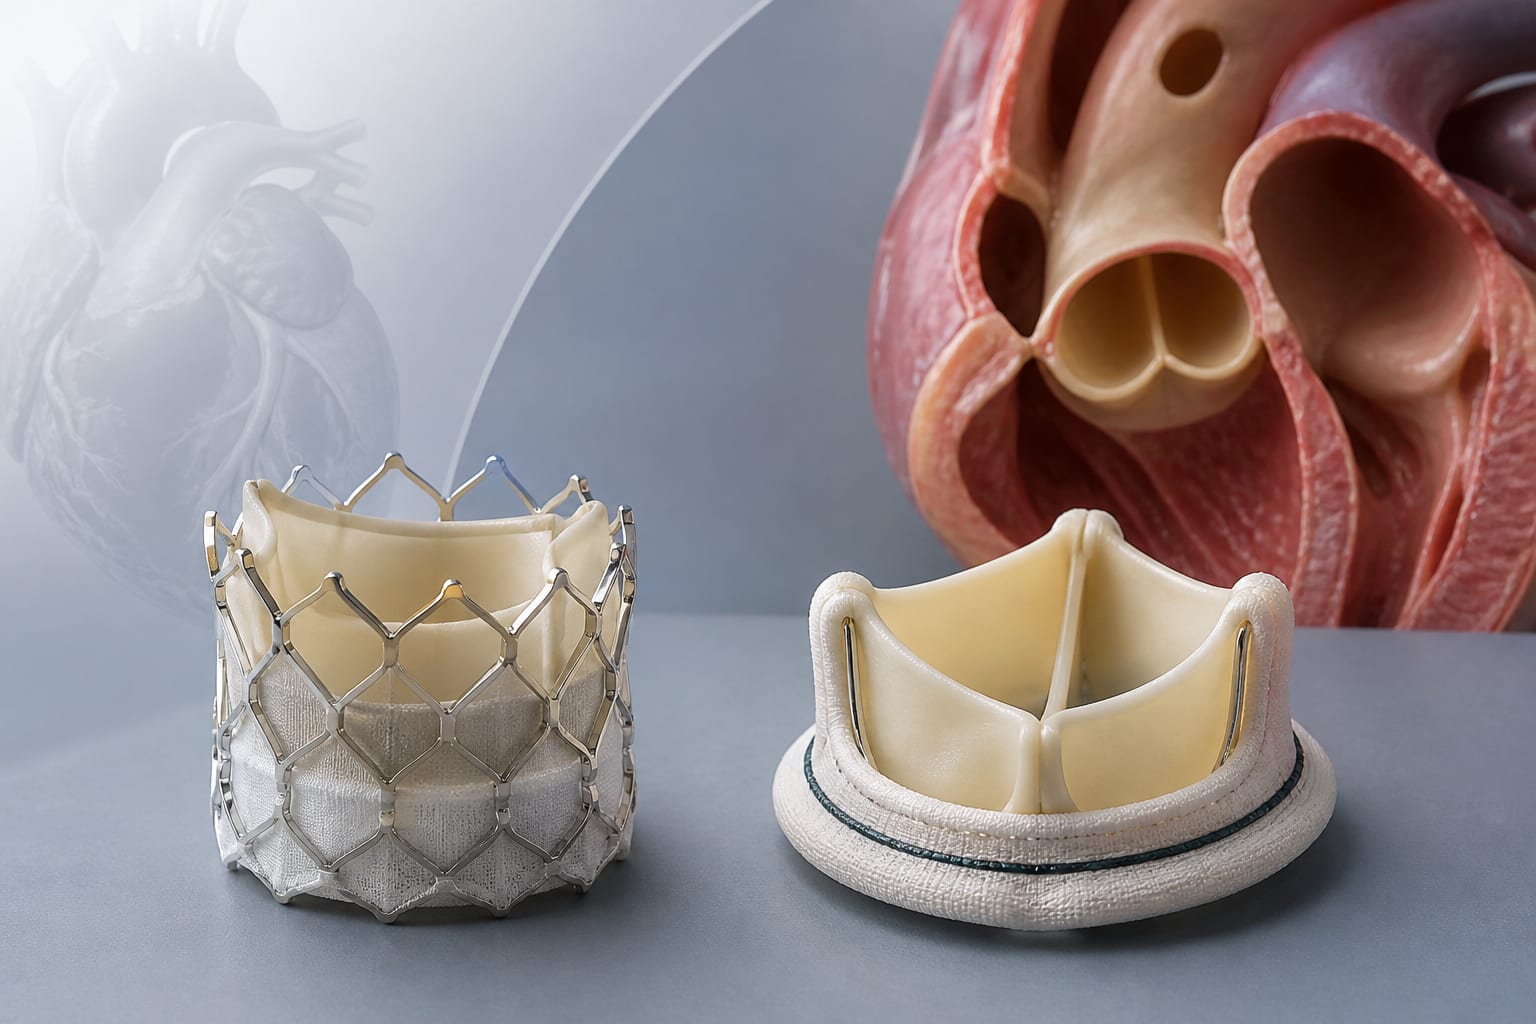
Respond to concerns about how valve choice and durability measures affect interpretation of seven-year PARTNER 3 results.
Approach:
Valve selection: Surgeons selected surgical bioprostheses they considered appropriate during trial enrollment, when Trifecta valves were regarded as an option without known late failure concerns.
Sensitivity analyses: The authors excluded Trifecta and Mitroflow valves to assess whether these devices affected comparisons of valve failure.
Durability measures: The reply contrasts reintervention with all-cause bioprosthetic valve failure (BVF), which includes reintervention, valve-related death, and irreversible severe valve dysfunction.
Key Findings:
After excluding Trifecta and Mitroflow valves, all-cause BVF rates were 6.9% with TAVR and 5.4% with surgery (P = .42).
BVF attributed to structural valve deterioration was 3.9% with TAVR and 3.4% with surgery (P = .69).
No PARTNER 3 participants were younger than 50 years, and 9.5% were aged 50 to 65 years; the authors therefore describe mechanical valve replacement as largely infeasible in this trial.
The authors state that newer balloon-expandable valves using Resilia tissue might have different durability outcomes, but characterize this possibility as hypothetical.
Interpretation:
The authors argue that reintervention alone may underestimate valve failure when clinical or patient-specific circumstances delay or prevent another procedure. They also state that durability may vary among valve platforms and that comparisons should reflect the range of platforms used in practice.
Limitations:
The proposed durability advantage of Resilia tissue is hypothetical in this reply.
The reply notes that PARTNER 3 included few patients aged 50 to 65 years and none younger than 50 years, limiting the relevance of mechanical-valve options to its population.
When patients with refractory AFib fall into a treatment gap, a collaborative new multidisciplinary clinic from Keck Medicine of USC gives them a way out.